

At a Glance
Prostate cancer is not one disease — it is a group of subtypes that behave differently. The most common is acinar adenocarcinoma (about 95% of cases), which is often slow-growing and may be suitable for active surveillance or focal therapy.¹ Ductal adenocarcinoma, small cell carcinoma, transitional cell carcinoma, squamous cell carcinoma and prostate sarcomas are rarer and typically more aggressive — they often don’t raise PSA and need urgent specialist input.
Key takeaways:
- Acinar adenocarcinoma — the most common type (~95%); slow-growing, low-risk cases may be managed with active surveillance.
- Ductal adenocarcinoma — less common but more aggressive; often presents with a normal PSA.
- Small cell carcinoma — a highly aggressive neuroendocrine tumour, typically treated with chemotherapy rather than hormone therapy.
- Transitional cell carcinoma — behaves like bladder cancer and follows a different pathway.
- Recurrent prostate cancer — salvage focal therapy (HIFU, NICE HTG667; NanoKnife, NICE HTG688) is an option for selected men with localised radiorecurrent tumours, with comparable long-term cancer control to salvage surgery and substantially fewer complications.²
Main types of prostate cancer
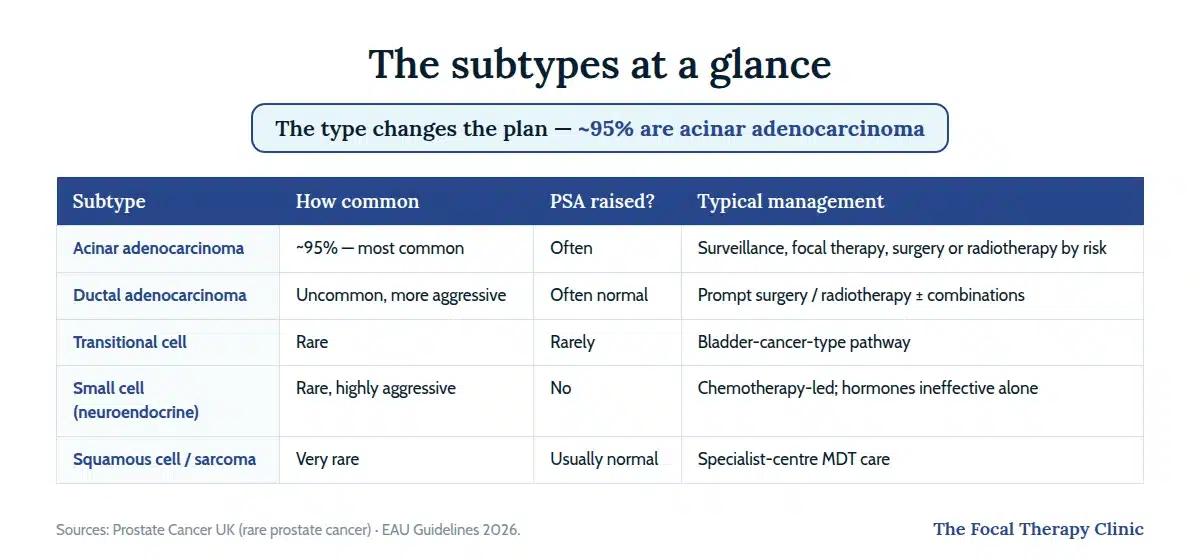
People often ask about “the four types of prostate cancer” — the main types are usually acinar adenocarcinoma, ductal adenocarcinoma, transitional cell carcinoma and small cell carcinoma. Each behaves differently and may need a different treatment plan.
The most common are the adenocarcinomas, which develop in the gland cells of the prostate and make up the vast majority of diagnoses. The subtypes differ in typical growth speed, presentation and treatment response.
Acinar adenocarcinoma
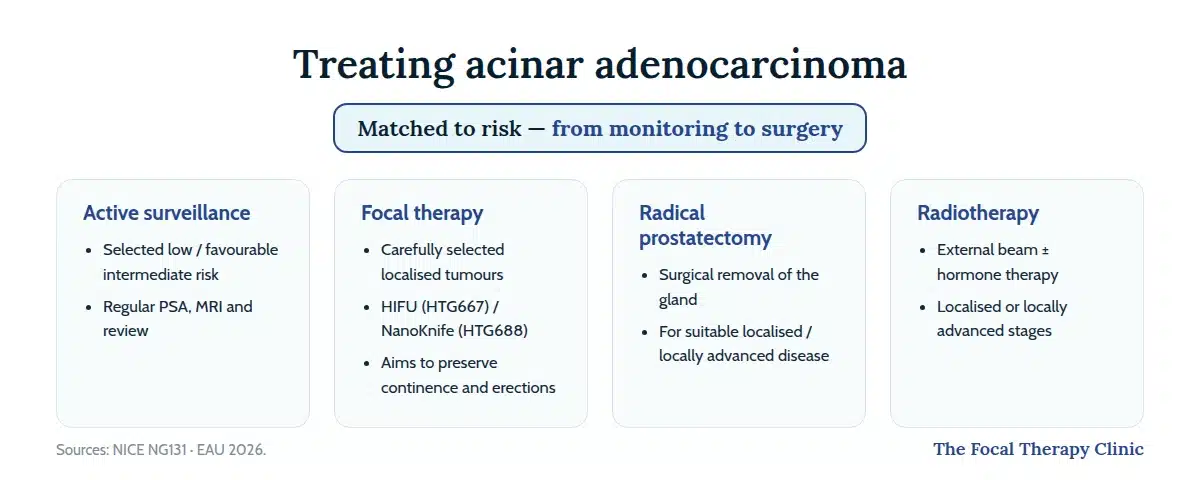
Acinar adenocarcinoma is the most common form. It begins in the glandular cells that produce the fluid component of semen, and PSA testing, MRI and biopsy often catch it early.
Depending on risk group and individual factors, doctors may recommend:
- Active surveillance — for selected men with low-risk or favourable intermediate-risk disease
- Focal therapy — for carefully selected men with localised tumours (HIFU, NICE HTG667, or NanoKnife, NICE HTG688)
- Radical prostatectomy — surgical removal of the prostate
- External beam radiotherapy — often combined with hormone therapy for localised or locally advanced disease
Many acinar adenocarcinomas grow slowly — some men live for years with careful monitoring alone.
Ductal adenocarcinoma
Ductal adenocarcinoma tends to grow faster and behave more aggressively than typical acinar disease. Importantly, men with this subtype may present with normal PSA levels, so it is often detected later, when urinary symptoms develop. Treatment may involve surgery, radiotherapy or combined therapies for advanced disease — and because of its aggressive nature it needs a prompt, comprehensive plan.
Rarer types of prostate cancer
Rare types differ significantly from standard adenocarcinomas. They often do not produce PSA, which makes early detection harder, and they almost always need specialist-centre care after urgent urology referral.¹
Transitional cell carcinoma
Also called urothelial carcinoma, this typically begins in the cellular lining of the bladder or urethra and biologically behaves like high-grade bladder cancer rather than conventional prostate cancer. Treatment may include radical surgery, chemotherapy for advanced cases, and radiotherapy.
| Feature | Transitional cell carcinoma | Acinar adenocarcinoma |
|---|---|---|
| Origin | Urothelial lining of the urethra or bladder | Prostate gland cells |
| PSA elevation | Rare | Common |
| Aggressiveness | Moderate to high | Highly variable |
| Main treatment | Surgery, chemotherapy, radiotherapy | Active surveillance, surgery, radiotherapy, or focal therapy |
Squamous cell carcinoma
Squamous cell carcinoma grows from flat, scale-like cells inside the prostate. It is very rare and does not behave like typical prostate cancer: PSA usually stays normal, diagnosis often comes only after significant symptoms, and it is generally resistant to standard hormone therapy. Teams may suggest surgery or radiotherapy, with systemic chemotherapy if the cancer has spread.
Small cell carcinoma
Small cell carcinoma is a neuroendocrine tumour — fast-growing and often already spread at diagnosis. The cells do not produce PSA, so standard blood tests are unreliable for detection or monitoring. Treatment usually relies on chemotherapy first, with radiotherapy and, in highly selected cases, surgery. Hormone therapy is generally ineffective when it occurs in isolation.
Sarcomas
Prostate sarcomas are extremely rare, forming in muscle, fat or connective tissue rather than glandular cells — and unlike adenocarcinomas they can affect younger men. PSA is usually normal. Examples include leiomyosarcoma and rhabdomyosarcoma; management combines aggressive surgery, tailored chemotherapy and radiotherapy under an expert multidisciplinary team.
Get Expert Advice & The Latest Research
Subscribe to our newsletter to receive the latest updates, expert insights, and breakthrough research on prostate cancer-delivered straight to your inbox.
How the type is identified
Dr Christos Mikropoulos explains the Gleason score — how biopsy grading works and what your score means for treatment choices.
The subtype is determined by a specialist pathologist examining biopsy tissue — usually collected by transperineal biopsy guided by MRI. For adenocarcinomas, the pathologist also assigns a Gleason score / Grade Group describing how aggressive the cells look, which combines with stage to shape the treatment plan. Rare subtypes may need additional specialised tests.
Recurrent prostate cancer

Prostate cancer can return after primary treatment — in the prostate area or as distant spread — and a rising PSA is frequently the first sign. Published estimates suggest biochemical recurrence occurs in roughly 20–50% of men within 10 years of radical local treatment, depending on initial risk.¹
Options are highly individualised and may include hormone therapy, salvage radiotherapy after surgery, or salvage focal therapy for selected men whose recurrence after radiotherapy is confined to the prostate. In a 2026 international matched comparison (923 patients), salvage focal therapy achieved 10-year cancer-specific survival of 92% versus 99% for salvage prostatectomy — no statistically significant difference — while salvage surgery carried substantially higher odds of complications.² Preparing questions for your urologist helps establish whether you are a suitable candidate.
Our consultants — 75+ years of combined focal therapy experience across 2,500+ procedures — provide second opinions for both new diagnoses and recurrence, including whether focal therapy has a role in your case.
Frequently Asked Questions
What is the most common type of prostate cancer?
Acinar adenocarcinoma — about 95% of all cases. It starts in the gland cells and is the type PSA testing, MRI and biopsy are best at finding, often at an early and treatable stage.¹
Can you have prostate cancer with a normal PSA?
Yes. Ductal adenocarcinoma often presents with normal PSA, and rare types (small cell, squamous, sarcoma) typically don’t produce PSA at all — one reason persistent urinary symptoms deserve investigation even with a normal blood test.
Which types can focal therapy treat?
Focal therapy (HIFU, NICE HTG667; NanoKnife, NICE HTG688) is used for carefully selected localised acinar adenocarcinoma — and, in specialist centres, as salvage treatment for localised recurrence after radiotherapy.² It is not a treatment for the rare aggressive subtypes.
Are the rare types hereditary?
Most prostate cancers, including rare subtypes, arise without a clear inherited cause, though family history and genes such as BRCA2 raise overall prostate cancer risk. Ask your team about genetic counselling if several close relatives have had prostate, breast or ovarian cancer.
How is the type of prostate cancer diagnosed?
Only by pathology: a specialist examines biopsy tissue under the microscope, identifies the cell of origin, and — for adenocarcinomas — assigns a Grade Group that guides treatment.
This content is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your urologist or other qualified health provider with any questions you may have regarding a medical condition.
References
- Prostate Cancer UK. Rare prostate cancer. 2022. https://prostatecanceruk.org/prostate-information-and-support/further-information/rare-prostate-cancer
- Light A, et al. Salvage Focal Therapy vs Radical Prostatectomy for Localized Radiorecurrent Prostate Cancer. JAMA Oncol. 2026;12(4):364–373.
- European Association of Urology. EAU Guidelines on Prostate Cancer. 2026. https://uroweb.org/guidelines/prostate-cancer
- National Institute for Health and Care Excellence. Prostate cancer: diagnosis and management (NG131). 2019, updated 2021. https://www.nice.org.uk/guidance/ng131
